l
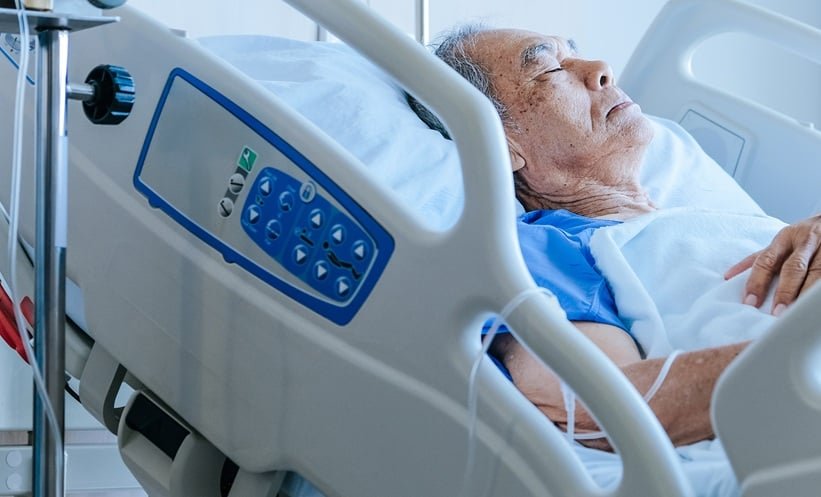
Liver transplant recipients may face a higher burden of impaired lung function and breathlessness than adults in the general population, according to a nationwide Danish matched cohort study. The findings suggest that chronic respiratory abnormalities may deserve greater attention during the long-term care of people who have undergone liver transplantation.
The study compared 512 adult liver transplant recipients with 2,010 age- and sex-matched participants from the general population. Researchers used spirometry to assess lung function and also evaluated patient-reported breathlessness.
The analysis found that liver transplant recipients had more than twice the adjusted odds of airflow limitation compared with matched controls. A second abnormal spirometry pattern, known as preserved ratio impaired spirometry (PRISm), was also substantially more common among transplant recipients. 0
What Did the Study Find About Lung Function?
Airflow limitation was identified in 10.7% of liver transplant recipients, compared with 7.1% of controls. After researchers adjusted for age, sex, ethnicity, cumulative smoking exposure and educational status, liver transplantation remained associated with more than twice the odds of airflow limitation.
The adjusted odds ratio was 2.06, indicating that the difference between the groups could not be explained by the measured demographic and smoking-related factors alone. However, because the study was observational, the findings demonstrate an association rather than proving that transplantation itself caused the respiratory abnormalities. 1
| Measure | Liver transplant recipients | Matched controls |
|---|---|---|
| Participants | 512 | 2,010 |
| Airflow limitation | 10.7% | 7.1% |
| PRISm | 23.8% | 11.8% |
PRISm Was About Twice as Common After Liver Transplantation
One of the notable findings concerned PRISm, or preserved ratio impaired spirometry.
PRISm describes a pattern in which the ratio between forced expiratory volume in one second (FEV1) and forced vital capacity (FVC) is preserved, but the measured FEV1 is lower than expected. It is not itself a diagnosis of a specific lung disease, but it can indicate abnormal respiratory physiology and may warrant clinical evaluation in the appropriate setting.
In the study, PRISm was found in 23.8% of liver transplant recipients, compared with 11.8% of controls. After adjustment for the measured confounding factors, recipients had nearly three times the odds of having this spirometric pattern compared with the general population controls. 2
Lung Volumes Were Also Lower in Transplant Recipients
The differences were not limited to the classification of airflow patterns.
Researchers reported that liver transplant recipients had an adjusted FEV1 that was 363 mL lower and an FVC that was 549 mL lower than the comparison group. FEV1 measures how much air a person can forcefully exhale in the first second of a breath, while FVC represents the total amount of air forcefully exhaled after a full inhalation.
These measurements provide objective evidence of differences in respiratory function between the groups, although the study cannot establish a single cause for those differences. 3
Why Might Lung Function Be Affected After Liver Transplantation?
The study does not establish that liver transplantation directly causes impaired lung function. Several factors may contribute to respiratory abnormalities in people with a history of advanced liver disease and transplantation.
People undergoing transplantation may have had significant illness before the procedure, including previous infections, reduced physical conditioning and other conditions that can affect respiratory health. Long-term medical treatment and complications occurring before or after transplantation may also influence overall health.
Importantly, the investigators found an association between a history of pulmonary infection and airflow limitation among transplant recipients. Those with a previous pulmonary infection had higher adjusted odds of airflow limitation, with an odds ratio of 2.23. 4
This finding is consistent with the broader concern that respiratory infections may have consequences beyond the acute episode, although the observational design does not prove that previous infection caused the later lung-function abnormality.
Breathlessness Was More Common Among Liver Transplant Recipients
The researchers also assessed dyspnea, or the sensation of breathlessness, using the modified Medical Research Council dyspnea scale.
Liver transplant recipients reported more frequent and more severe breathlessness than the matched participants from the general population. This is clinically relevant because spirometry findings and symptoms can provide complementary information: an abnormal lung-function test may identify physiological impairment, while breathlessness indicates how respiratory limitations are experienced in daily life. 5
Persistent or unexplained breathlessness in a transplant recipient therefore should not automatically be attributed to reduced fitness or aging. Depending on the individual circumstances, clinicians may consider respiratory assessment and other potential causes.
What Is Spirometry and Why Is It Important?
Spirometry is a commonly used pulmonary function test that measures how much air a person can breathe out and how quickly they can do so.
Two important measurements are:
- FEV1: The volume of air forcefully exhaled during the first second of the test.
- FVC: The total volume of air forcefully exhaled after taking a full breath.
The relationship between FEV1 and FVC helps clinicians identify patterns that may suggest airflow limitation. Other patterns, including PRISm, can indicate impaired lung function without meeting the conventional definition of airflow obstruction.
In the Danish study, spirometry allowed researchers to identify differences that might not be apparent from symptoms alone. 6
How Does This Fit With Earlier Research?
The new findings add to research from the same Danish research programme examining respiratory health and inflammation among liver transplant recipients.
A separate 2026 analysis of 335 liver transplant recipients from the Danish Comorbidity in Liver Transplant Recipients (DACOLT) study reported airflow limitation in 11.6% and PRISm in 24.5% of participants. Researchers also found that higher high-sensitivity C-reactive protein (hs-CRP), a marker of systemic inflammation, was associated with PRISm and lower FEV1 and FVC. 7
That study found that participants with hs-CRP above 3 mg/L had more than twice the adjusted odds of PRISm. Higher hs-CRP was also associated with lower FEV1 and FVC after adjustment for relevant factors. The authors suggested that systemic inflammation may be involved in the biological processes underlying impaired lung function, but this remains an area for further investigation. 8
Does Liver Transplantation Cause Lung Disease?
The study does not establish that liver transplantation itself causes chronic lung disease.
This distinction is important. The research was observational and compared existing characteristics between transplant recipients and matched controls. Although researchers adjusted for several potential confounding factors, there may be other differences between the groups that influence respiratory function.
For example, the study cannot completely separate the effects of the underlying liver disease, pre-transplant health, previous infections, medications, smoking history and other medical conditions from the effects associated with having received a transplant.
The findings therefore support greater clinical awareness of respiratory health after transplantation rather than demonstrating a direct cause-and-effect relationship.
Why the Findings Matter for Long-Term Transplant Care
Liver transplantation can be life-saving, but successful transplantation does not necessarily eliminate the need for long-term monitoring of other organ systems.
The study suggests that respiratory health could be one of the areas deserving attention during long-term follow-up, particularly when recipients report persistent breathlessness, reduced exercise tolerance or other respiratory symptoms.
The researchers described chronic pulmonary abnormalities as a potentially underrecognized comorbidity among liver transplant recipients. Recognising symptoms and considering appropriate pulmonary assessment could help clinicians identify patients who may benefit from further evaluation. 9
What Should Liver Transplant Recipients Do If They Have Breathlessness?
Breathlessness can have many causes, and its significance depends on how severe it is, when it occurs and whether it is new or worsening.
Liver transplant recipients with persistent or unexplained breathing difficulty should discuss the symptom with their transplant or treating medical team. Depending on the clinical situation, doctors may consider lung-function testing, imaging, assessment for infection, cardiovascular evaluation or investigation of other potential causes.
Sudden or severe breathing difficulty, chest pain, bluish discoloration, confusion or other acute symptoms require urgent medical assessment.
Could Pulmonary Monitoring Become More Important After Transplantation?
The study does not establish that every liver transplant recipient requires routine lung-function testing. Instead, it highlights a potentially important area for clinical awareness.
The relatively high prevalence of PRISm in the transplant group raises questions about whether some patients may have respiratory abnormalities that are not routinely recognised. Future studies will need to determine how these spirometric patterns change over time, whether they predict clinically important outcomes and which factors are responsible.
Longitudinal research could also clarify whether lung function improves, remains stable or declines after transplantation and how factors such as infections, inflammation, physical activity, medications and pre-existing lung disease influence these trajectories.
Key Takeaways From the Liver Transplant Lung Study
- Liver transplant recipients had more respiratory abnormalities than age- and sex-matched general population participants.
- Airflow limitation affected 10.7% of recipients compared with 7.1% of controls.
- PRISm affected 23.8% of recipients compared with 11.8% of controls.
- After adjustment, transplant recipients had more than twice the odds of airflow limitation.
- FEV1 and FVC were also lower among transplant recipients.
- A history of pulmonary infection was associated with increased odds of airflow limitation among recipients.
- Recipients reported more frequent and severe breathlessness than matched controls.
- The observational study shows associations and does not prove that transplantation itself caused the lung abnormalities.
Bottom Line
A nationwide Danish study suggests that impaired lung function may be more common among liver transplant recipients than previously recognised. Recipients had more than twice the adjusted odds of airflow limitation, while PRISm occurred in 23.8% compared with 11.8% among matched controls. Previous pulmonary infection was also associated with airflow limitation in the transplant group. 10
The findings do not establish that liver transplantation causes chronic lung impairment. Instead, they point to the importance of recognising respiratory symptoms and considering pulmonary health as part of long-term care after transplantation. Further research is needed to determine the causes of these abnormalities and their long-term clinical significance.
“`11
For breaking news and live news updates, like us on Facebook or follow us on Twitter and Instagram. Read more on Latest Health on thefoxdaily.com.
COMMENTS 0